Plants first, variety over volume. Aim for 30+ different plant foods a week — vegetables, fruits, legumes, nuts, seeds, whole grains, herbs, and spices all count. Rotate colors instead of the same “safe” salad daily. Fermented foods (kimchi, sauerkraut, tempeh) support gut health, tied to hormone metabolism.
Rethinking protein. Skip the 180–200g targets aimed at bodybuilders. Simple formula: body weight in pounds ÷ 2 = a reasonable daily minimum in grams (roughly 75–100g for a 150 lb woman). Regular strength training? Lean toward the higher end. Spread it across meals — plant proteins (lentils, beans, tofu, edamame) count too, and bring fiber and phytoestrogens along.
KEY NUTRIENTS + SOURCES:
Calcium: dairy or fortified plant milk, leafy greens, tofu, canned salmon/sardines with bones, almonds
Vitamin D: fatty fish, egg yolks, fortified foods, sun exposure — many benefit from a supplement (ask your doctor)
Omega-3s: fatty fish, walnuts, chia and flax seeds
Women-specific research points to: heavy strength work, short strategic intensity, and less moderate “in-between” cardio.
Strength, 2–3x/week. Go heavy when you can — struggling to finish 3 reps by your 5th set is a good benchmark — but consistency matters more than the number. Options: free weights (squats, deadlifts, rows, presses), bodyweight (push-ups, step-ups, glute bridges), resistance bands, strength classes (BODYPUMP, barre, functional fitness), or Pilates. Two full-body sessions a week, 20–30 minutes each, is enough. Heavy lifting won’t “bulk you up” — that takes far more volume and food than this.
Add bone-specific jump training. Three 10-minute sessions a week of low-amplitude jumps (jumping jacks, small box jumps, jump squats) — one of the most effective moves for bone density.
Long, easy-paced sessions as your main training can blunt strength gains. Keep intervals short and infrequent — 1–2x/week, ~30 minutes: sprint intervals (30 sec hard/90 sec easy × 6–8), hill sprints, or hard bike/rower work where you can’t talk. Save easy walks and swims for recovery days.
Fuel how your body prefers. A pre-workout protein + carb snack (Greek yogurt with fruit, a shake with a banana) helps some feel steadier. Others — especially the 5am class crowd — feel strongest fasted; the science isn’t settled. Trust what works.
Don’t skip: balance/mobility work (single-leg stands, yoga, tai chi) and real rest days — recovery matters more now.
Ready to put this into practice?
Schedule an appointment with your health coach for personalized guidance on eating and exercising through this transition.
While the physicians at Carolina Total Wellness are thrilled that the use of hormone replacement therapy (HRT) in menopause has gained acceptance in conventional medicine and social media conversations, there is one area that is still causing some confusion.
If you are taking or considering taking HRT you may hear two similar-sounding words: progesterone and progestin. They are not the same—and the difference can matter for your long-term safety.
Progesterone is the natural hormone your ovaries made before menopause. The form used in many modern regimens is micronized progesterone—chemically identical to your body’s own hormone. You may hear micronized progesterone described as bio-identical progesterone.
Progestins are synthetic (lab-made) compounds designed to mimic some of progesterone’s effects. Common examples include medroxyprogesterone acetate (MPA), the progestin used in the large Women’s Health Initiative (WHI) trials.
Both can protect the uterine lining when you take estrogen (important if you still have a uterus). At appropriate doses, natural progesterone and synthetic progestins appear similarly effective at preventing endometrial hyperplasia. [1]
The WHI showed that conjugated estrogen plus the synthetic progestin MPA raised breast cancer incidence, while estrogen alone (in women without a uterus) did not and was linked to lower breast cancer rates over long-term follow-up. [2]
Later research comparing formulations suggests the progestogen type is a key factor. Observational data and reviews indicate that estrogen combined with micronized progesterone is associated with a lower breast cancer risk than estrogen plus synthetic progestins. [3][4] One meta-analysis found roughly one-third lower relative breast cancer risk with progesterone versus synthetic progestins when each was paired with estrogen. [4]
Reviews also point to a similar or possibly more favorable profile for cardiovascular and metabolic outcomes with micronized progesterone compared with many synthetic progestins. [1][5][6] Natural progesterone is the preferred choice when breast or cardiovascular risk factors are a concern. [7][6]
What This Means for You
Hormone therapy remains the most effective treatment for bothersome vasomotor symptoms and can support bone, brain, cardiovascular and genitourinary health when started in appropriate candidates. [8][9] If you have a uterus, a progestogen is required with systemic estrogen.
Choosing micronized progesterone (often taken orally at bedtime) is one practical way many clinicians individualize therapy toward a potentially better breast and overall safety profile while still protecting the endometrium. Transdermal estradiol plus oral micronized progesterone is a common evidence-aligned combination.
Therapy should always be personalized—dose, route, timing, and your personal risk factors. If you are interested in HRT or have questions about your current HRT therapy, the physicians at Carolina Total Wellness can help.
Creatine is a naturally occurring substance found in the body, primarily in muscle tissue. It plays a crucial role in providing energy for high-intensity, short-duration activities such as weightlifting, sprinting, and other explosive exercises. In recent years, creatine has gained popularity as a dietary supplement, particularly among athletes and bodybuilders. This article will discuss the benefits and risks of using creatine as a supplement.
Most adults, especially women, under-eat protein. Aim for 0.4–0.9 grams per pound of ideal body weight daily. A 150-pound adult needs about 60–90 grams per day (20–30 grams per meal). At 200 pounds, that’s 80–150 grams daily or 25–40 grams at 3–4 meals, depending on your goals.
Animal-based proteins are typically more complete and easier to digest. Choose organic, non-GMO, wild-caught fish, pasture-raised poultry, grass-fed beef, and pasture-raised eggs.
Plant-based options like lentils, hemp seeds, and quinoa can form a complete diet when combined thoughtfully. Vegetarians and vegans should eat a variety of plant proteins to meet amino acid needs.
Choose whole foods whenever possible. For protein powders, look for organic or grass-fed sources with minimal ingredients—no added sugar, colorings, gums, or “natural flavors.” Pure Paleo Bone Broth Protein, WheyCool Grass-Fed Protein, and Mikuna Chocho Plant Protein are excellent options.
Muscle synthesis is optimized when protein intake is spread evenly throughout the day—20–35 grams per meal. Start with a protein-rich breakfast to balance blood sugar, cortisol, and energy.
Before workouts, have a small snack with protein, carbs, and healthy fats—like apple slices with nut butter. After strength training, consume 20–30 grams of protein within 20–30 minutes to maximize recovery. Plan ahead so quality protein is available during this window.
Hormones and Aging
With age, hormones like growth hormone, testosterone, and estrogen decline, making muscle harder to maintain—but not impossible. Nutrients such as creatine, magnesium, vitamin D, and omega-3s support hormone sensitivity and muscle health. Resistance training naturally boosts anabolic hormones and signals the body to preserve lean tissue. Pairing consistent strength training with adequate protein amplifies results.
Your Longevity Organ
Think of muscle as your longevity organ. Supporting it means combining strength training, quality protein, restorative sleep, and stress management. Small daily choices compound over time.
Avoiding soy? Sensitive to dairy? Recovering from injury or surgery? Your protein needs will change throughout life. At your next visit, ask your CTW care team about an InBody composition scan to see where you’re starting and create a plan for your goals. Your team is here to help you build strength, resilience, and a foundation for lifelong health.
The hormonal shifts that accompany perimenopause and menopause lack a clear instruction manual, often leaving many women in a continuous cycle of trial and error when it comes to managing their symptoms. Fortunately, one of the most potent tools available for regaining control of your hormones is the food you consume. Certain foods contribute to hormone balance and can help alleviate perimenopause and menopause symptoms, while others can disrupt your body’s hormonal equilibrium.
When essential nutritional elements are lacking, hormonal imbalances can arise, leading to mood swings, weight gain, hot flashes, and reduced libido. The primary hormones affected during perimenopause and menopause are estrogen, progesterone, insulin, and testosterone, and your dietary choices can significantly impact these hormones. For instance, excessive sugar consumption can elevate insulin levels, trigger inflammation, and exacerbate nearly every perimenopausal symptom. On the other hand, incorporating vegetables, fruits, nuts, and seeds into your diet can provide phytonutrients and healthy fats that aid in managing even the most challenging menopause symptoms.
While there’s no one-size-fits-all diet, several foods have proven beneficial for most people seeking to balance their hormones:
1. Brassica (aka cruciferous) Vegetables: These include broccoli, cauliflower, kale, and cabbage, which contain indole-3-carbinol—a compound that helps metabolize estrogen in the gut and liver. This can be particularly helpful in addressing estrogen dominance.
2. Healthy Fats: Avocados, nuts, seeds, and fish are rich inomega-3 fatty acids and other fats crucial for reducing inflammation and supporting hormone production, especially progesterone.
3. Fiber-Rich Foods: Fiber is essential for gut health, which plays a critical role in hormone balance. Low-starch fruits and veggies, nuts, seeds, and whole grains can boost your fiber intake, aiding in estrogen metabolism and blood sugar regulation.
However, there are also foods and drinks that should be limited or avoided:
1. Caffeine: Excess caffeine can lead to increased stress hormone production and elevated cortisol levels, potentially exacerbating fatigue and estrogen levels.
2. Processed Carbs and Sugar: As tolerance to sugar decreases with age, limiting simple carbohydrates and sugars (like table sugar, baked goods, and packaged foods) becomes crucial for managing blood sugar and insulin levels.
3. Alcohol: Even moderate alcohol consumption can disrupt hormones, affect brain aging, and lead to elevated insulin levels and estrogen dominance.
4. Gluten: Gluten sensitivity can contribute to gut issues, thyroid problems, and autoimmune conditions, making it advisable to assess its impact on your health
Balancing your diet can ease the transition into perimenopause and menopause, regardless of whether you’re just beginning to experience symptoms or are already in the midst of them. By making thoughtful dietary choices, you can navigate this phase of life with greater vitality and well-being.
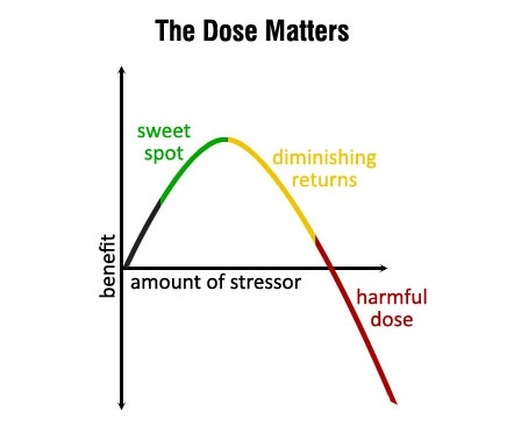
What doesn’t kill you makes you stronger. We’ve all heard the saying before. Science has revealed it is surprisingly accurate when it comes to our health and longevity.
Hormesis is the idea that short, intermittent bursts of certain stressors can start a cascade of cellular processes that slow aging, improve overall health and make you more resilient, both physically and mentally. It is a hot topic in longevity research right now.
We all know that chronic stress caused by relationship issues, financial problems and working too many hours is detrimental to our health. However, hormetic stressors are controlled and acute, triggering healthy adaptive responses.
What does all this mean in real life? Hormesis is the common thread found in some popular health and fitness trends such as HIIT (high intensity interval training), cold exposure, heat therapy and intermittent fasting. Prolonged doses of these behaviors are not healthy or sustainable. For example, if you spend too much time in a sauna you will become dehydrated. But, in short bursts, the bodily stress caused by these practices are enough to bring about health benefits such as reducing inflammation, supporting elimination of toxins, repairing DNA, combatting oxidative stress, repairing cellular damage and reducing risk of cancer.
Here are three ways to strategically stress your body and reap the rewards:
HIIT – Do a HIIT workout 1-3 times a week. HIIT workouts are intermittent bursts of intense effort for 30 seconds, followed by 15 seconds of rest. These workouts are usually short, around 15-20 minutes. You can easily find these HIIT videos on YouTube.
Hot or Cold Therapy – Infrared sauna is a great way to heat up and sweat out some toxins. It also reduces inflammation and pain. In contrast, ice baths, cold showers and the new cryotherapy chambers that are popping up everywhere will cool you down quicky. Cold therapy is also known for reducing inflammation and pain. Both types of therapies may help strengthen the immune system.
Intermittent Fasting – Fasting triggers a cellular “clean up” response called autophagy. Autophagy results in several health benefits such as lowered cholesterol, reduced blood pressure and reduced inflammation. For many, a 16:8 intermittent fasting schedule (16 hours of fasting followed by an 8 hour feeding window) works well. However, we recommend that you experiment with the timing to see what works best for you.
Be aware that adding stress (even the good type!) to our lives can backfire if done at the wrong time. When life is already very stressful, it is best to wait until a better time when you are more relaxed to try out these new practices.
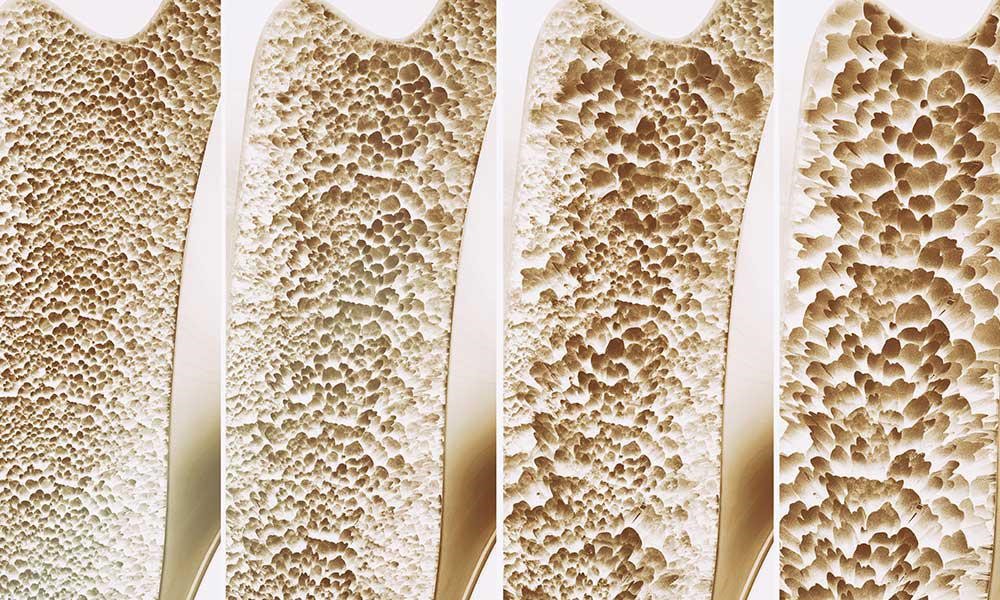
Osteoporosis refers to a condition where bones become brittle. A report from the Surgeon General states in the US 54 million Americans are at risk for osteoporosis, and 10 million Americans already have osteoporosis. Although women make up 80% of osteoporosis cases, men still get osteoporosis. Each year 1.5 million people suffer a fracture from bone loss, and if this is a hip fracture, mortality in the first year can be as high as 40%, with higher mortality rates in men than in women. Starting in childhood, there is a fine balance between the building up and breaking down of bones coordinated beautifully between cells named osteoblasts and osteoclasts, respectively. If there is too much osteoclast activity, then there is an increased amount of breakdown of bone as seen in inflammation. There is also this misconception that it is the lack of calcium causing osteoporosis. It is actually calcium balance and not the total calcium which is important in osteoporosis.
Risk factors for osteoporosis include: 1) Aging: Inflammation is a normal process of aging, which increases with age, in functional medicine, this is termed “inflamm-aging”. 2) Diet- SAD: Diet (Standard American Diet) is very inflammatory, upregulating the immune system. Consumption of excess amounts of sugar, alcohol, caffeine, salt, and soda all can lead to bone loss due to demineralization of the bones. A leaky gut can drive inflammation to the point of bone resorption. 3) Lifestyle: Stress, smoking, inactive lifestyle can all contribute to an increased rate of breakdown of bone compared to a build-up of bone. 4) Genes: For instance, Celiac disease predisposes to osteoporosis due to poor absorption of minerals. 5) Gender: Being a female increases the risk, since it is usually seen after menopause because estrogen is protective for the bones as well as the brain and the heart. During menopause estrogen declines and there is no further protection for the bones. 6) Medications: Steroids, proton pump inhibitors (omeprazole, pantoprazole, esomeprazole), cancer drugs, thyroid hormone, cyclosporine, heparin, and warfarin.
Testing for osteoporosis is done thru a DEXA scan. It is also known as a Dual Energy X-ray Absorptiometry, or Bone Density scan, a simple X-ray where the hip and the spine bone density are measured. T-score represents the difference in your bone density from the average bone density of healthy young adults. If the T-score is -1 to -2.5 it is considered osteopenia, if <-2.5 osteoporosis. Osteopenia refers to the beginning of osteoporosis, meaning “bone poverty”.
Treatment of osteoporosis by conventional medicine involves using strong drugs, sometimes too strong which may even cause a break in the bones.
1. Bisphosphonates: i.e., Fosamax, Boniva, Actonel, and Reclast target areas of high turnover where the osteoclasts, cells which break down old bone, absorb bisphosphonate and hence their activity is slowed down and there is a reduction in bone breakdown. Side effects: bone, joint, muscle pain, nausea, gastric ulcer, stress fracture of the thigh bone
2. SERM: Selective estrogen receptor modulator- i.e.Raloxifene, acts like estrogen in some parts of the body but blocks the effects of estrogen in other parts. Increases bone density and reduces the risk of spine fractures, but it has not been shown to decrease the risk of non-spinal fractures. Raloxifene also decreases the risk of invasive breast cancer. Side effects: hot flashes, leg cramps, or blood clots in the legs or lungs. Raloxifene is not recommended for premenopausal women.
3. Parathyroid hormone molecule: i.e. Teriparatide, abaloparatide stimulates new bone formation, rather than preventing bone breakdown. Because of potential safety concerns, particularly an increased risk of bone cancer in rats, the use of this drug is restricted to men and women with severe osteoporosis—who have a high risk of a fracture—and can be given for no more than two years. Side effects: uncommon but may include leg cramps, headaches, dizziness, high blood calcium, and high urinary calcium (with an increased risk of kidney stones). This medication is not recommended for premenopausal women.
4. Romosuzumab: Bone-building medication that is given once a month as pair of injections by a doctor or nurse. Treatment is given once a month for twelve months and is then followed by another medication to prevent bone loss. Romosozumab reduces the risk of spine fractures and non-spine fractures, including hip fractures. Romosozumab may increase the risk of heart attack or stroke—including fatal heart attack or stroke—and it should not be given to women who have had a heart attack or stroke in the past year. It is approved for the treatment of osteoporosis in women past the time of menopause who are at high risk for fracture, defined as a history of osteoporotic fracture, multiple risk factors for fracture, or failure or intolerance to other available osteoporosis therapies. It may cause side effects such as headaches or joint pain.
5. Estrogen hormone therapy: Prevents bone loss and reduces the risk of fracture in the spine and hip. It can also relieve other symptoms of menopause, such as hot flashes and vaginal dryness. Estrogen is usually given in pill form, although it is also available in other forms such as a skin patch or gel. Studies show that the risks of oral estrogen therapy—including heart attack, stroke, blood clots, and breast cancer—may outweigh its benefits in many older women, depending upon the dose and specific preparation. For this reason, estrogen therapy is not usually prescribed solely for fracture prevention.
A comprehensive functional medicine approach to the evaluation of osteoporosis takes the form of blood, saliva, stool, and urine testing. Low-grade inflammation can be assessed thru blood work by checking hs-CRP, HgA1C, ESR, CMP, CBC, and essential fatty acids. Blood work for vitamin D and osteocalcin is necessary since vitamin D helps absorb calcium into the bones and osteocalcin is a biomarker for functional vitamin K deficiency. Bone resorption can be evaluated by urine N-telopeptide. Stool analysis to evaluate the gut is also important since calprotectin in stool provides information about inflammation in the gut. Gut microbes are responsible for making vitamin K, which is necessary for having better bone density. Saliva testing for hormones would provide information about the levels of estradiol, testosterone, DHEA, cortisol, and progesterone.
A comprehensive functional medicine approach to the treatment of osteoporosis is first and foremost prevention. It is recommended by conventional doctors to get a DEXA scan once a woman turns 65, however, it may be too late for some since many risk factors play a role in developing osteoporosis. It is ideal to have a DEXA scan around ages 30-35 as a baseline since this is the time of peak bone mass, and then another one a year after menopause to compare the degree of bone loss to get ahead of the condition.
Osteoporosis refers to a condition where bones become brittle. A report from the Surgeon General states in the US 54 million Americans are at risk for osteoporosis, and 10 million Americans already have osteoporosis. Although women make up 80% of osteoporosis cases, men still get osteoporosis. Each year 1.5 million people suffer a fracture from bone loss, and if this is a hip fracture, mortality in the first year can be as high as 40%, with higher mortality rates in men than in women.
Starting in childhood, there is a fine balance between the building up and breaking down of bones coordinated beautifully between cells named osteoblasts and osteoclasts, respectively. If there is too much osteoclast activity, then there is an increased amount of breakdown of bone as seen in inflammation. There is also this misconception that it is the lack of calcium causing osteoporosis. It is actually calcium balance and not the total calcium which is important in osteoporosis.
Risk factors for osteoporosis include: 1) Aging: Inflammation is a normal process of aging, which increases with age, in functional medicine, this is termed “inflamm-aging”. 2) Diet- SAD: Diet (Standard American Diet) is very inflammatory, upregulating the immune system. Consumption of excess amounts of sugar, alcohol, caffeine, salt, and soda all can lead to bone loss due to demineralization of the bones. A leaky gut can drive inflammation to the point of bone resorption. 3) Lifestyle: Stress, smoking, inactive lifestyle can all contribute to an increased rate of breakdown of bone compared to a build-up of bone. 4) Genes: For instance, Celiac disease predisposes to osteoporosis due to poor absorption of minerals. 5) Gender: Being a female increases the risk, since it is usually seen after menopause because estrogen is protective for the bones as well as the brain and the heart. During menopause estrogen declines and there is no further protection for the bones. 6) Medications: Steroids, proton pump inhibitors (omeprazole, pantoprazole, esomeprazole), cancer drugs, thyroid hormone, cyclosporine, heparin, and warfarin.
Testing for osteoporosis is done thru a DEXA scan. It is also known as a Dual Energy X-ray Absorptiometry, or Bone Density scan, a simple X-ray where the hip and the spine bone density are measured. T-score represents the difference in your bone density from the average bone density of healthy young adults. If the T-score is -1 to -2.5 it is considered osteopenia, if <-2.5 osteoporosis. Osteopenia refers to the beginning of osteoporosis, meaning “bone poverty”.
Treatment of osteoporosis by conventional medicine involves using strong drugs, sometimes too strong which may even cause a break in the bones.
1. Bisphosphonates: i.e., Fosamax, Boniva, Actonel, and Reclast target areas of high turnover where the osteoclasts, cells which break down old bone, absorb bisphosphonate and hence their activity is slowed down and there is a reduction in bone breakdown. Side effects: bone, joint, muscle pain, nausea, gastric ulcer, stress fracture of the thigh bone
2. SERM: Selective estrogen receptor modulator- i.e.Raloxifene, acts like estrogen in some parts of the body but blocks the effects of estrogen in other parts. Increases bone density and reduces the risk of spine fractures, but it has not been shown to decrease the risk of non-spinal fractures. Raloxifene also decreases the risk of invasive breast cancer. Side effects: hot flashes, leg cramps, or blood clots in the legs or lungs. Raloxifene is not recommended for premenopausal women.
3. Parathyroid hormone molecule: i.e. Teriparatide, abaloparatide stimulates new bone formation, rather than preventing bone breakdown. Because of potential safety concerns, particularly an increased risk of bone cancer in rats, the use of this drug is restricted to men and women with severe osteoporosis—who have a high risk of a fracture—and can be given for no more than two years. Side effects: uncommon but may include leg cramps, headaches, dizziness, high blood calcium, and high urinary calcium (with an increased risk of kidney stones). This medication is not recommended for premenopausal women.
4. Romosuzumab: Bone-building medication that is given once a month as pair of injections by a doctor or nurse. Treatment is given once a month for twelve months and is then followed by another medication to prevent bone loss. Romosozumab reduces the risk of spine fractures and non-spine fractures, including hip fractures. Romosozumab may increase the risk of heart attack or stroke—including fatal heart attack or stroke—and it should not be given to women who have had a heart attack or stroke in the past year. It is approved for the treatment of osteoporosis in women past the time of menopause who are at high risk for fracture, defined as a history of osteoporotic fracture, multiple risk factors for fracture, or failure or intolerance to other available osteoporosis therapies. It may cause side effects such as headaches or joint pain.
5. Estrogen hormone therapy: Prevents bone loss and reduces the risk of fracture in the spine and hip. It can also relieve other symptoms of menopause, such as hot flashes and vaginal dryness. Estrogen is usually given in pill form, although it is also available in other forms such as a skin patch or gel. Studies show that the risks of oral estrogen therapy—including heart attack, stroke, blood clots, and breast cancer—may outweigh its benefits in many older women, depending upon the dose and specific preparation. For this reason, estrogen therapy is not usually prescribed solely for fracture prevention.
A comprehensive functional medicine approach to the evaluation of osteoporosis takes the form of blood, saliva, stool, and urine testing. Low-grade inflammation can be assessed thru blood work by checking hs-CRP, HgA1C, ESR, CMP, CBC, and essential fatty acids. Blood work for vitamin D and osteocalcin is necessary since vitamin D helps absorb calcium into the bones and osteocalcin is a biomarker for functional vitamin K deficiency. Bone resorption can be evaluated by urine N-telopeptide. Stool analysis to evaluate the gut is also important since calprotectin in stool provides information about inflammation in the gut. Gut microbes are responsible for making vitamin K, which is necessary for having better bone density. Saliva testing for hormones would provide information about the levels of estradiol, testosterone, DHEA, cortisol, and progesterone.
A comprehensive functional medicine approach to the treatment of osteoporosis is first and foremost prevention. It is recommended by conventional doctors to get a DEXA scan once a woman turns 65, however, it may be too late for some since many risk factors play a role in developing osteoporosis. It is ideal to have a DEXA scan around ages 30-35 as a baseline since this is the time of peak bone mass, and then another one a year after menopause to compare the degree of bone loss to get ahead of the condition.
Once you have osteoporosis then the treatment is as follows:
Exercise: At least 3 days a week, if you don’t use your bones you will lose them. Weightlifting, bands, core strengthening, and yoga all help with building up bone mass and also help preserve balance.
Optimize vitamin D levels: In osteoporosis, you need higher levels of vitamin D, ideally 80-100. This usually amounts to 5000 IU daily and needs to be taken along with vitamin K2 which helps absorb the Calcium into the bones in place of the arteries.
Diet: Eliminate “bone dissolvers”: excess protein, SAD processed diet, excess salt. Obtain Calcium from your diet as much as possible and not supplements. Add more greens to your diet, herring, mackerel, sesame seeds, and chia seeds are all excellent sources of calcium.
Hormones: Low testosterone and low estrogen can cause bone loss, and higher levels of FSH in menopause are associated with higher osteoclast activity. Hormone supplementation may help.
Nutraceuticals: Trace minerals are extremely important in building bone, such as magnesium, zinc, boron, manganese, copper, and silicon. If you are taking Calcium then make sure it’s in a microcrystalline hydroxyapatite complex which provides bone-enhancing factors such as growth factors, peptides, and mucopolysaccharides.
Many of us have too much glucose (blood sugar) in our system and are not aware of it. Glucose enters our bloodstream mainly through the sweet or starchy foods we eat. The conventional medicine community has taught for many years that unless you are diabetic or pre-diabetic your blood sugar levels are not important. However, more recent, cutting-edge science and the increased use of continuous glucose monitors (CGM’s) have proven that everyone needs to pay more attention to glucose levels. A CGM is a small device that attaches to the back of your arm and monitors blood glucose on a continuous basis. You can obtain a CGM through a prescription or purchase one online through websites such as Signos, Veri and Nutrisense. I wore a CGM for several weeks recently and found it very informative in understanding how my food choices affect my blood sugar levels. For example, I realized how breaking my fast with a low carb meal was very helpful in avoiding the spike that can occur after fasting for 16 hours.
Symptoms of uncontrolled glucose can include fatigue, food cravings and brain fog. Long term effects of uncontrolled glucose can include hormonal dysfunction, acne, wrinkles and infertility. Over time the development of type 2 diabetes, cancer, dementia, PCOS and heart disease can occur.
There are several easy modifications you can make to your diet that flatten the glucose curve that occurs after eating. These modifications include:
Eating fiber first. Have your vegetables before your protein and/or starch.
Ingesting apple cider vinegar before eating carbs
Avoiding sugar on an empty stomach. Have it after a meal instead.
Getting some type of movement in after eating a meal high in carbs. A walk or even just some air squats will do.
There is a new book out about blood glucose called The Glucose Revolution written by Jessie Inchauspe. The author goes into depth about the huge impact glucose has on our health. She then presents several ways to control our blood sugar more effectively. The book also includes tips on how to handle cravings, better choices in alcohol and how to read ingredient labels.
Jessie Inchauspe has an Instagram account (glucosegoddess) that continues the education on controlling glucose and gives lots of actional advice. This may help provide you with some motivation to jump start a healthier lifestyle in 2023. Our health coaches and physicians at Carolina Total Wellness are also always available to provide you with personalized advice on improved blood sugar control.























 Learn More


